Back Pain Doctor
Slipped Disc and Bulging Disc
Written by Dr Joshua Hatch, Musculoskeletal GP, RACGP Fellow, Diploma in Musculoskeletal Medicine (FSEM UK).
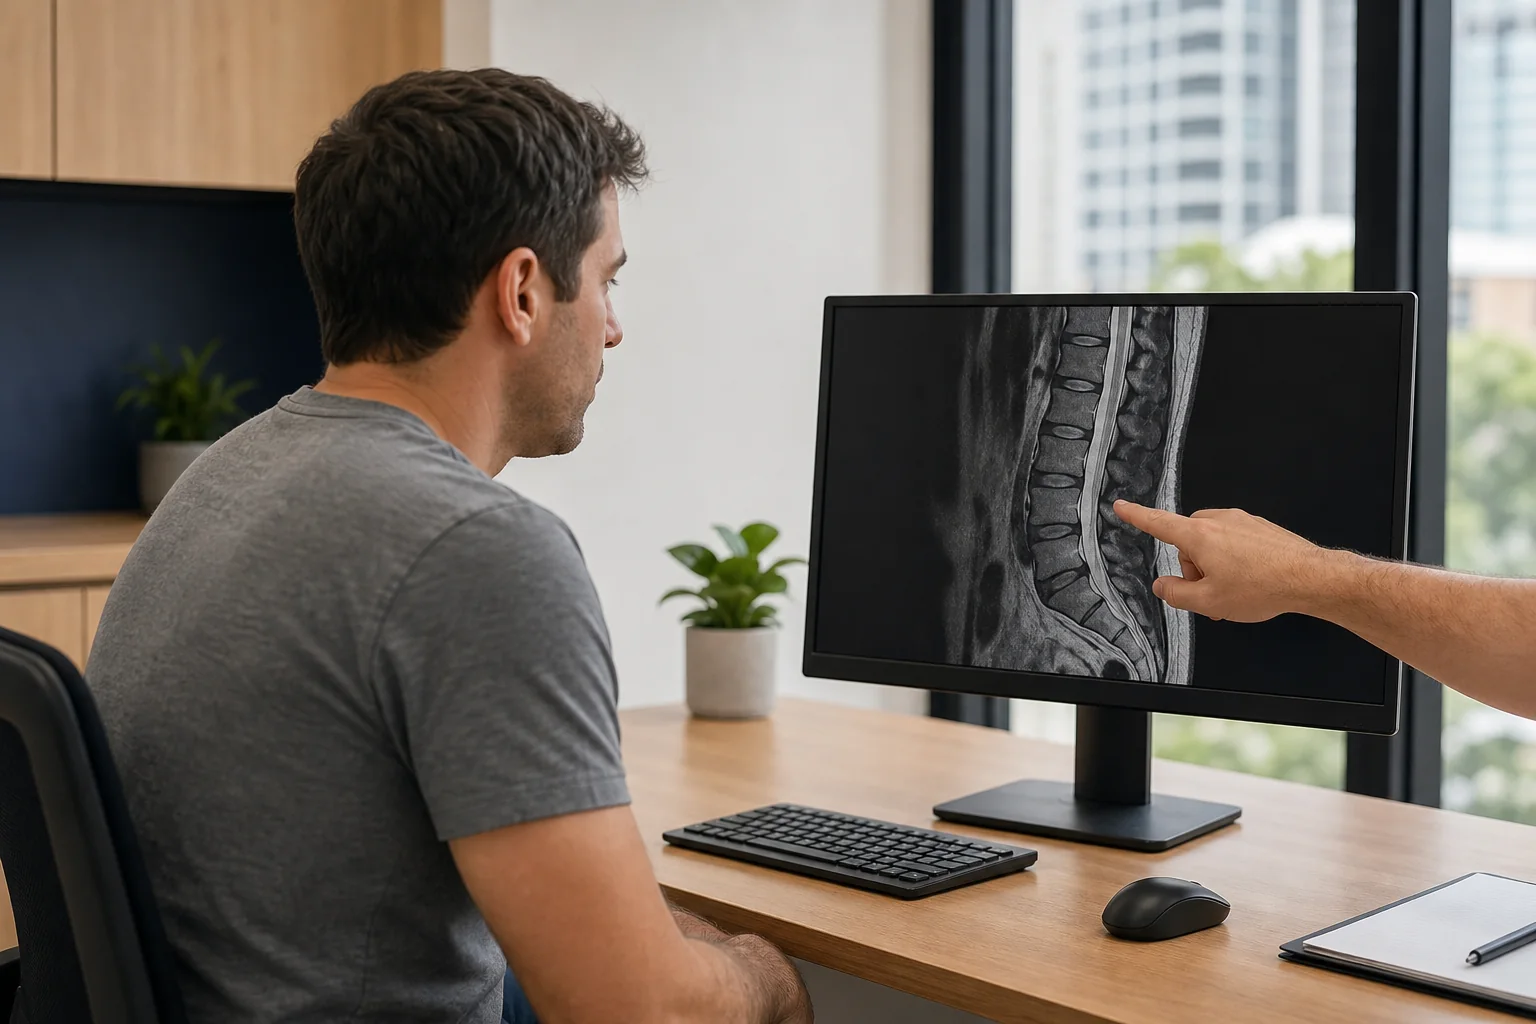
The language in a lumbar MRI report can sound more alarming than the clinical reality. Intervertebral discs are strong, flexible structures between the spinal bones. They change with age and load, and those changes may be visible on a scan whether or not the person has pain.
What the scan terms mean
- “Slipped disc” is everyday language, not a literal event. Discs do not slide in and out of place. The term usually refers to a herniated disc.
- Disc bulge describes a broad extension of the disc beyond its usual boundary.
- Disc protrusion or extrusion describes a more focal displacement of disc material; these sit within the medical category of disc herniation.
- Nerve compression matters when its level and side fit leg pain, sensation changes, weakness and examination findings.
These terms describe appearance, not automatically the source or severity of pain. A systematic review of asymptomatic people found disc bulges and other degenerative features were common and became more frequent with age. Australia’s Low Back Pain Clinical Care Standard likewise advises that disc bulges, fissures and protrusions are very common in people without pain and are usually features of ageing.
Treat the person, not the report
Routine imaging is not usually the first step for uncomplicated low back pain because it often does not change early care. Assessment looks for the pattern of back and leg symptoms, neurological findings, function and the uncommon features that require urgent investigation. When imaging is appropriate, its findings are matched to that clinical picture.
Most episodes improve with time, sensible activity and progressive rehabilitation. Prolonged bed rest is unhelpful. If a disc is irritating or compressing a nerve, treatment may also address pain while recovery occurs, and persistent disabling symptoms or progressive weakness can warrant a spinal surgical opinion.
For more detail on a focal herniation causing sciatica, see the lumbar disc herniation guide. For leg-dominant nerve pain and its other possible causes, see sciatica.
Common symptoms
- Lower back pain, which may or may not be related to a disc finding on a scan
- Sciatica—pain travelling from the buttock into one leg
- Pins and needles, numbness or altered sensation in the leg or foot
- Leg weakness or pain aggravated by coughing, sneezing, bending or sitting
Commonly seen in
Evidence for twelve treatment options in slipped disc and bulging disc
This is not a fixed ladder or a package of treatments. Every option is assessed independently against this diagnosis, including treatments with limited direct research that may still be reasonable for a clearly defined tissue target. The evidence level, likely benefit, risks, cost and alternatives are weighed at consultation.
Foundation — diagnosis, education and rehabilitation
The part of care with the broadest relevance. For many people it is enough on its own; other options are judged against it, not automatically added after it.
Diagnosis, education and progressive rehabilitation Working out what is driving the pain, explaining what your imaging does and does not mean, and building a graded loading plan you can actually follow. Core care
What it involves
Assessment to identify the likely pain source, an explanation of what the diagnosis means, adjustment of the loads that aggravate it, and a progressive strength and conditioning plan — with weight management where that is clinically relevant.
What the evidence shows
Every high-quality guideline says the same thing. The American College of Physicians makes a strong recommendation that chronic low back pain be treated first with exercise and multidisciplinary rehabilitation rather than drugs or procedures (Qaseem, Ann Intern Med 2017). An overview of 15 primary-care guidelines found consistent agreement on education, staying active, exercise and reassurance, and on discouraging routine imaging (Oliveira, Eur Spine J 2018). For neck pain the strongest effects also belong to exercise, with strengthening of the neck and upper quadrant showing a moderate short-term effect (Sterling, J Clin Med 2019). Adding pain-science education to exercise improves pain, disability and fear of movement over exercise alone (Bonatesta, J Pain 2021).
Pairing reviewed 2026-09-02.
Where it fits for you
Understanding why the back hurts, and moving well, does more than anything injected. Imaging is used to answer a specific question, not as a starting point — degenerative findings are near universal and frequently unrelated to the pain.
Muscle and symptom-modifying options
Useful only when the examination identifies the tissue they target or when short-term pain control creates a useful rehabilitation window.
Wet needling and trigger point injection (trigger point injection) A fine needle into a tender band of muscle, with a small volume of dilute glucose solution injected through it. Worth discussing
What it involves
The needle is placed into the tender muscle band and a small volume of 5% glucose with 0.02-0.08% lignocaine is injected. Often done in the same visit as your assessment, and usable where the tender area sits deeper. Dry needling — the same technique with nothing injected — is not offered here.
What the evidence shows
The muscle around a painful disc is a separate, treatable target from the disc itself. A randomised trial of 100 people with lumbar disc herniation found trigger-point-directed needling improved pain, movement and quality of life more than standard acupuncture (Li, Zhen Ci Yan Jiu 2024). Against that, the largest trial of trigger point injection in low back pain randomised 180 people to injection or standard care alone and found no difference in pain or function (Lajeunesse, Ann Emerg Med 2025). No trial has used the dilute glucose solution used here.
Pairing reviewed 2026-09-07.
Where it fits for you
Directed at tender muscle, never at the disc. Offered as an adjunct where examination reproduces part of your pain from a muscle band, and only alongside the loading work that does the real job.
Ultrasound-guided injections Guidance means we can see the needle reach the target. What goes into the needle depends on the diagnosis. Small, short-term effect
What it involves
The injection is performed under ultrasound so the needle can be watched into the target structure. What is injected is decided by the diagnosis — and corticosteroid is used sparingly, for the reasons set out below.
What the evidence shows
The same evidence as the disc herniation guide, and the same caveat: these are epidural corticosteroid injections given under X-ray or CT by a radiologist or pain specialist, not ultrasound-guided injections. Twenty-five placebo-controlled randomised trials in 2,470 people found epidural corticosteroid probably better than a placebo injection for short-term leg pain, by 4.9 points on a 0 to 100 scale (95% CI -8.8 to -1.1), and for short-term disability by 4.2 points (-6.0 to -2.2), with moderate-quality evidence and mostly minor side effects (Oliveira, Spine 2020). A review of 90 randomised trials put it at roughly one extra person helped for every four treated in the short term, with too little evidence to judge pain beyond six months (Armon, Neurology 2025). An injection does not shrink a bulge or repair a disc.
Pairing reviewed 2026-09-17.
Where it fits for you
Not performed here. Considered as a referral where leg pain is severe or is not settling, and framed as buying a working window rather than fixing the disc. A bulging disc on a scan is a common finding in people with no pain at all, so the decision follows the symptoms rather than the image. See the note on cortisone.
V-ACTOR vibration therapy (vibration therapy) Low-frequency vibration applied over tender muscle. Not a shockwave, despite sharing the machine. Plausible — no studies
What it involves
A vibration handpiece is moved over the tender muscle and fascia for a few minutes. It runs from the same STORZ MASTERPULS icon console as radial shockwave but is a separate handpiece delivering a different, gentler form of energy. No needles, no anaesthetic, no downtime.
What the evidence shows
No published clinical trial of this device in this condition. It is a vibration handpiece delivered from the same console as radial shockwave, and the rationale is myofascial rather than tendon- or bone-directed.
Pairing reviewed 2026-08-30.
Where it fits for you
A comfort measure used within a session where muscular tightness is limiting movement. Never the reason for the appointment, and not a substitute for the treatments that do have evidence.
Energy-based treatment options
Radial pressure wave, focused shockwave and EMTT have different targets and different evidence. They are assessed separately rather than treated as one category.
Radial or focused shockwave? Read the overviewRadial shockwave (radial pressure wave) Broad treatment across tender muscle and fascia, close to the surface. Not for the disc
What it involves
A handpiece is moved over the tender tissue while ballistic pressure pulses are delivered, using a transmitter head chosen for the tissue — including heads shaped for fascia and for the muscle either side of the spine. The pulse is strongest at the skin and weakens with depth, so this is mainly a myofascial treatment, though it can reach deeper in some areas. No anaesthetic, no downtime, usually a course of sessions about a week apart.
What the evidence shows
The same tested absence as the disc herniation guide this page describes in plainer terms: searching lumbar disc herniation, disc herniation, sciatica and radiculopathy against shockwave, shock wave and ESWT returned nine records and no trial of shockwave for a bulging or herniated disc. Benefit has been shown in non-specific chronic low back pain, where 22 studies of 1,749 patients found pain -1.14 (95% CI -1.47 to -0.80) and Oswestry disability -6.01 (-7.97 to -4.05), still lower at three months (Wu, Medicine 2023), and ten randomised trials of 455 people found pain at one month a standardised mean difference of -0.81 (-1.21 to -0.42) with no serious adverse events (Yue, Biomed Res Int 2021). Neither tells you anything about a disc.
Pairing reviewed 2026-09-13.
Where it fits for you
Not a treatment for the disc itself. It is offered for the tender back and buttock muscle that commonly comes with a disc problem, and that muscular component is often a bigger part of the day-to-day pain than the disc is.
Focused shockwave (ESWT) A true shock wave converging at depth — for tendon, joint, ligament and bone. Only if relevant
What it involves
A focused system generates an acoustic shock wave that converges at a focal point set at a defined depth, concentrating the energy where the target is. This is the form we use for tendon, joint, ligament and bone. Typically four to six sessions about a week apart, no anaesthetic and no formal downtime.
What the evidence shows
Focused shockwave is not aimed at a disc, a facet joint or a nerve root, and there is no trial evidence for it in these conditions.
Pairing reviewed 2026-08-30.
Where it fits for you
Considered only where examination finds a separate tender muscle or tendon contributing to the pain.
EMTT (magnetotransduction therapy) High-energy magnetic pulses applied over the area. Painless, no contact. Plausible — no studies
What it involves
You sit with the applicator positioned over the area for a short session. Painless, no gel or contact required, and usually delivered as a course — commonly alongside shockwave.
What the evidence shows
There are no published randomised trials of EMTT in this condition, or in any musculoskeletal condition, that we can point to. The supporting work is laboratory work: EMTT increased tenocyte proliferation, migration and collagen expression in cultured human tendon cells (Mancini, Int J Mol Sci 2025). The nearest human evidence for a related electromagnetic therapy is negative — a randomised trial of pulsed electromagnetic field therapy added to eccentric exercise for Achilles tendinopathy found no improvement in outcome scores or tendon neovascularity over eccentric exercise alone (Ko, Orthop J Sports Med 2024).
Pairing reviewed 2026-08-30.
Where it fits for you
Offered only as an adjunct alongside treatment that does have evidence, never as the plan itself, and only after that gap is explained. Much of the EMTT literature is manufacturer-affiliated, which is part of why we describe it this way.
Biologic and joint injection options
Each injection is assessed independently for the named diagnosis. Cost, uncertainty, likely benefit, risks and alternatives are part of the decision.
Platelet-rich plasma (PRP) Your own blood, concentrated and injected under ultrasound guidance. Evidence mixed
What it involves
Blood is taken from your arm, spun to concentrate the platelets, and injected into the target under ultrasound guidance in the same appointment.
What the evidence shows
The trials are of platelet-rich plasma delivered as an epidural or transforaminal injection at the nerve root, not the soft-tissue injections done here. In a randomised double-blind trial of 46 patients with a prolapsed lumbar disc and radiculopathy, steroid was clearly better at one week, platelet-rich plasma better at six weeks and six months, and the two were indistinguishable at one year (Gupta, Asian Spine J 2024). Meta-analyses agree the two are broadly comparable overall (Muthu, Exp Biol Med 2025) while disagreeing about the early weeks (Wang, J Orthop Surg Res 2025), and the certainty of the evidence has been graded very low (Kubrova, Biomedicines 2022).
Pairing reviewed 2026-09-03.
Where it fits for you
Not offered here. A bulging disc on a scan is a common finding that is frequently unrelated to the pain, so the first question is whether the disc is the problem at all — not which injection to place near it.
Prolotherapy (dextrose) A course of dextrose injections into and around the structure and its attachments. Evidence mixed
What it involves
Hypertonic dextrose is injected at the tender ligament and tendon attachments, and into the joint where relevant, usually as a series of treatments a few weeks apart.
What the evidence shows
The trials in disc-related back pain disagree. A 2026 systematic review of twelve studies found pain relief lasting six to twenty-four months, though only three were randomised (Nazwar, J Anaesthesiol Clin Pharmacol 2026), while an American Pain Society evidence review found prolotherapy not effective for low back pain (Chou, Spine 2009) and the one randomised epidural prolotherapy trial showed no benefit past forty-eight hours (Desai, Pain Practice 2020).
Pairing reviewed 2026-09-05.
Where it fits for you
Nothing about this injection repairs a bulging disc. It is considered only where tender ligaments or attachments are contributing to the pain, and only after core care.
Viscosupplementation (hyaluronic acid) A gel-like injection into an arthritic joint. Widely used, and genuinely contested. Not used here
What it involves
One or a short series of hyaluronic acid injections into the joint under ultrasound guidance.
What the evidence shows
Hyaluronic acid has been put into a lumbar disc, but only as the carrier for something else. In trials of intradiscal stem-cell injection it is the fluid the cells are suspended in and one of the comparison arms rather than the treatment being tested — 100 people in the first (Amirdelfan, Spine J 2020) and 404 in a larger trial whose main measure of success was not met (Beall, Spine J 2025). Its other use is as an additive to a nerve root block, where in 44 people it reduced the flare of pain in the first fortnight but made no difference by six weeks or to function (Ko, Spine J 2018). Neither of those is lubrication of a joint.
Pairing reviewed 2026-09-20.
Where it fits for you
Not offered for this problem. A bulging disc is not a joint that can be lubricated, and bulges are common findings on scans in people with no pain at all.
Nerve-targeted options
Relevant when examination identifies a superficial neuropathic pattern or a compressed peripheral nerve—not simply because pain is present.
Lyftogt perineural therapy (perineural injection therapy) A series of small dilute dextrose injections just under the skin, over tender superficial nerves. Only if relevant
What it involves
Small injections of low-concentration dextrose, usually 5%, placed just beneath the skin along tender superficial nerves. Given as a series of short sessions.
What the evidence shows
The dextrose nerve evidence is in peripheral entrapment — carpal tunnel and cubital tunnel — not in nerve root compression from the spine.
Pairing reviewed 2026-08-30.
Where it fits for you
Not a treatment for a compressed nerve root. Considered only where a separate peripheral entrapment is also present.
Ultrasound-guided nerve hydrodissection Fluid placed around a nerve to free it from the surrounding tissue. Only if relevant
What it involves
Under ultrasound, fluid is placed in the plane around the nerve to separate it from the tissue that is tethering or compressing it.
What the evidence shows
The dextrose nerve evidence is in peripheral entrapment — carpal tunnel and cubital tunnel — not in nerve root compression from the spine.
Pairing reviewed 2026-08-30.
Where it fits for you
Not a treatment for a compressed nerve root. Considered only where a separate peripheral entrapment is also present.
This is general information only and suitability is assessed individually. Treatments with limited or condition-dependent evidence may still be discussed, but only with clear explanation of the uncertainty, the expected benefit, risks, cost and alternatives. Red flags, progressive neurological symptoms or suspected serious pathology require a different pathway.
Every treatment above is described in full on the non-surgical treatments page, including what each one is used for and what the evidence supports. Ratings apply to the named diagnosis; an adjacent muscle, tendon, joint or nerve problem is assessed as a separate target. The method behind the ratings, and the treatments we do not offer, are set out on the evidence page.
Corticosteroid injection is reviewed separately for each diagnosis.
Cortisone reliably reduces pain in the short term, and that can be genuinely useful when pain is stopping you sleeping or moving enough to rehabilitate. Beyond that window the picture changes. A systematic review of 41 randomised trials and 2,672 participants found that corticosteroid injection reduced pain in the short term but that the effect reversed at intermediate and long term; in pooled analysis for lateral epicondylalgia the short-term effect was large (SMD 1.44, 95% CI 1.17 to 1.71) while no intervention was favoured at 26 weeks (-0.40, -0.67 to -0.14) and at 52 weeks (-0.31, -0.61 to -0.01) (Coombes, Lancet 2010). In a randomised trial in lateral epicondylalgia, 83 per cent of the corticosteroid group had completely recovered or much improved at one year against 96 per cent given a placebo injection, and recurrence ran at 54 per cent against 12 per cent; adding physiotherapy made no significant difference at one year (Coombes, JAMA 2013). In joints, repeated corticosteroid injections have been associated with cartilage loss. It does not repair anything.
So we do not build treatment plans around it. Where an injection is the right call, we review the specific diagnosis and target, discuss what is being injected and why, keep the number low, and pair it with the loading work that changes the longer-term course.
When we would still consider it
- Pain severe enough to block rehabilitation
- A clear inflammatory or bursal target on imaging
- A specific short-term goal — a trip, a procedure, a return to work
- Diagnostic use, where the response tells us where the pain is coming from
When a cortisone injection is worth doing, and when it is not
Other back conditions
Pain in the same area can come from more than one source, and the label matters less than what the examination and history point to. These are the other guides for this region.
Frequently asked questions
Are a slipped disc and a bulging disc the same thing?
Does a bulging disc always cause pain?
When is a disc problem an emergency?
Ready for a clearer plan for your back or musculoskeletal pain?
Book an assessment with Dr Joshua Hatch.
Your assessment focuses on understanding the likely source of your pain and the most appropriate non-surgical options for your diagnosis, with the aim of reducing pain and improving function.
Book an appointment