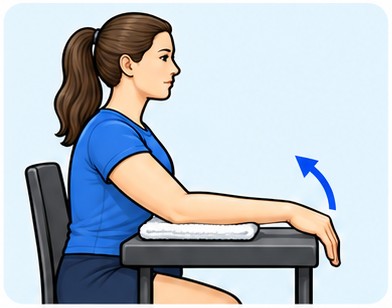
1. Active wrist extension
5–10 easy repetitions.
- Action.
- Support the forearm palm down. Lift the hand gently from the wrist, then return.
- Technique.
- Move without added weight. Avoid forcing an end position.
Back Pain Doctor
Back Pain Doctor · Dr Joshua Hatch · backpaindoctor.com.au
Osteoarthritis of the Elbow
Progressive rehabilitation and graded return to activity
Before you start
Use this programme for an assessed condition when exercise is appropriate. An acute fracture, tendon rupture, unstable injury or recent operation may need different restrictions. Any specific protection or surgical instructions take priority.
Elbow arthritis may cause stiffness and pain at the ends of movement. Gentle range work and strength support function but cannot remove bone spurs.
Maintain useful elbow and forearm movement, then rebuild lifting capacity.
Mild familiar discomfort up to about 3 out of 10 may be acceptable if steady and movement stays controlled. Sharp or increasing pain is a reason to stop. Pain, swelling and function should return to baseline by the next morning. This is a practical guide, not a proven safety threshold.
Avoid forceful stretching against a hard block. Locking, increasing ring or little finger numbness, or weakness requires review.
When symptoms increase
Reduce the provoking movement, repetitions or resistance by about one third to one half. Keep other comfortable activity where appropriate. Do not add harder exercise until the response is stable. A sudden major change needs assessment.
Begin with one set if needed. Practise gentle movement daily if it helps; perform strengthening on 2–3 non-consecutive days each week. Rest 30–60 seconds between easy sets. You do not need to force the full dose on the first day.
5–10 easy repetitions.

5–10 easy repetitions.

5–10 each way.
Ready for Phase 2
Gentle range is comfortable and any splint or injury restrictions permit progression. There should be no increasing numbness, locking or swelling.
Avoid forceful stretching against a hard block. Locking, increasing ring or little finger numbness, or weakness requires review.
Use 2–3 non-consecutive strength days each week and rest 60–120 seconds between sets. Begin with a resistance that leaves a few controlled repetitions in reserve. Add repetitions first, then a small amount of resistance.
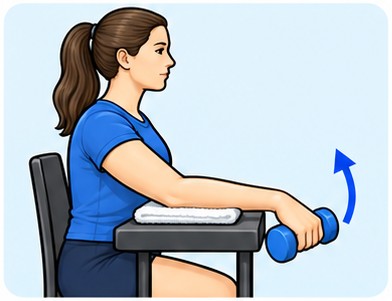
2–3 sets of 8–12.
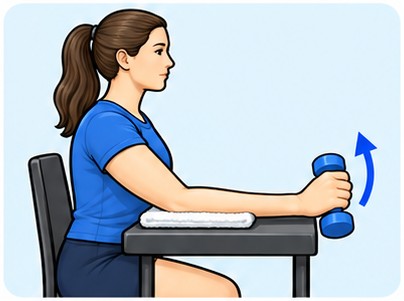
2–3 sets of 8–12.

5–10 holds of 3–5 seconds.
Ready to add Phase 3
Light resistance is controlled with no next-morning worsening. Nerve symptoms or catching must be settled before repeated gripping.
Maintain useful elbow and forearm movement, then rebuild lifting capacity. When the top repetition range is easy on several sessions, increase resistance slightly and return to the lower end. Keep the range and movement quality consistent. Avoid increasing weight, repetitions and frequency together.
Continue strength work on 2–3 days weekly. Add one new demand at a time. If impact is part of the programme, allow 48–72 hours between demanding impact sessions initially and reduce the strength volume on those days.
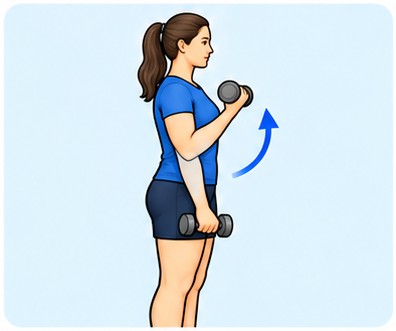
2–3 sets of 8–12.
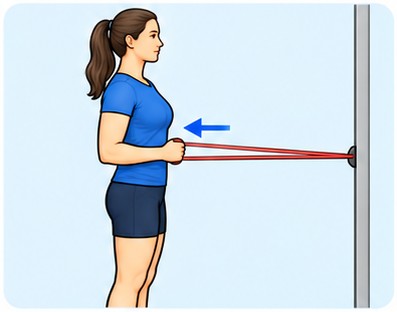
2–3 sets of 10–15.
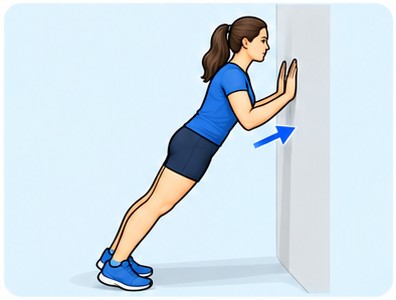
2–3 sets of 8–12.
Ready to increase real activity
Build the actual required grip, pinch, wrist position and task duration. Repeated numbness, locking or loss of strength requires review rather than further load.
Increase carrying, pushing and repetitive work in controlled steps. The final stage should reflect the real task: carrying, lifting, stairs, walking, running or sport. You can finish rehabilitation for daily life without needing to complete running or jumping drills that your activity does not require.
Increase carrying, pushing and repetitive work in controlled steps.
| Stage | What to build |
|---|---|
| Everyday function | Use comfortable movement and daily tasks in manageable blocks. Establish a stable next-day response. |
| More demanding activity | Increase duration before adding substantial load, speed, hills or more complex positions. |
| Specific work or sport | Practise the actual task at reduced intensity and duration, then progress it on separate occasions. |
| Full participation | Complete the required activity repeatedly with control and confidence, without a significant next-day flare. Injury-specific clearance may still be needed. |
Use 2–3 non-consecutive strength days, with comfortable mobility or easy activity between them. Start a new activity at less than your usual duration or intensity. Keep harder sessions apart and leave more recovery time when symptoms are still increased. For tendon loading, the condition-specific frequency on the exercise pages takes priority.
Continue useful strengthening about twice weekly after recovery, alongside regular activity. Break long or repetitive tasks into manageable periods and maintain a plan for a temporary flare. A flare does not automatically mean new damage, but a different or progressive symptom needs assessment.
Seek prompt assessment for a new cold or discoloured hand, progressive numbness, muscle wasting, loss of strength, a fixed locked digit or a rapidly enlarging lump. A hot red swollen joint with illness needs urgent review. Book reassessment if progress has stalled for 4–6 weeks, function is deteriorating or the same progression repeatedly causes a flare. Do not wait for that interval when a warning symptom is present.
Condition-specific exercise research is limited. This programme uses available guidance and cautious clinical extrapolation. Exercise selection, sets and progression checks are practical starting prescriptions rather than a trial-validated complete protocol.
Dr Joshua Hatch | The Back Pain Doctor. Handout prepared 1 Nov 2026.
